// blog
What a Patient Imaging Portal Needs: A Checklist for Imaging Centers
A patient imaging portal needs online booking that knows the scanners and rooms, a browser DICOM viewer for the patient’s own images, the radiologist’s reports, a safe way to share studies with other doctors, a way to bring in prior studies from other hospitals (CDs and ZIPs), and the basics underneath: secure sign-in, access control, audit logs and encryption. Build booking and reports first, then images and sharing.
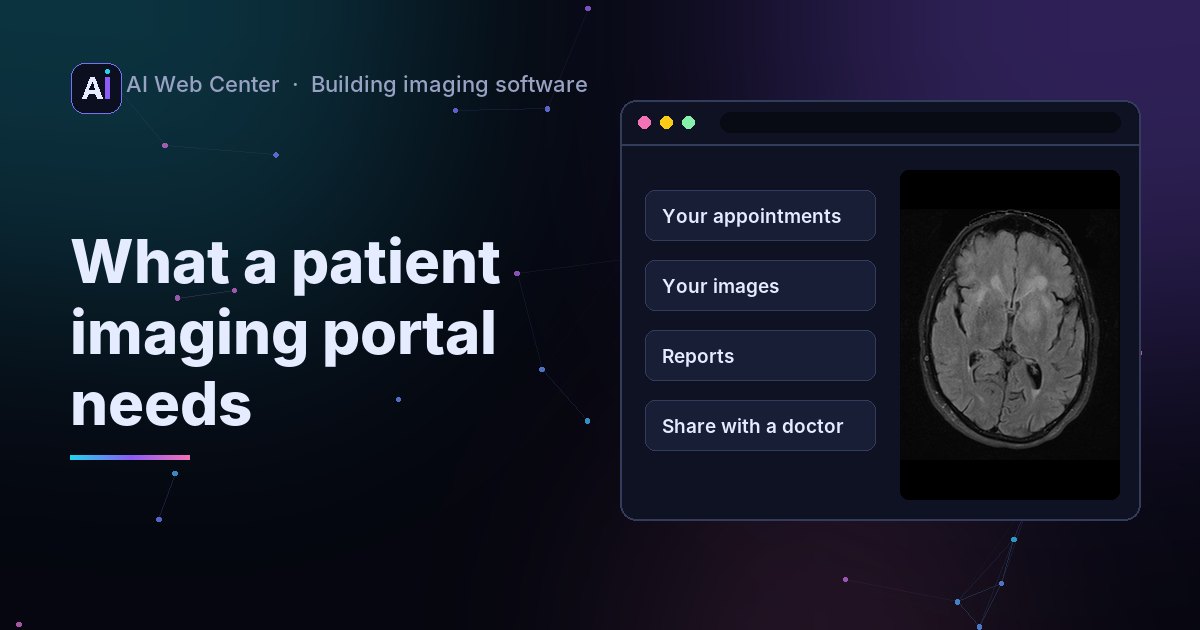
Our Lumenwell Imaging example is a working sketch of a patient imaging portal: booking by scan room, and the patient’s images in a real DICOM viewer. Building it surfaced the list below: what a real portal needs, and in what order.
1. Booking that knows the equipment
Booking a scan isn’t booking a doctor. The exam decides the scanner: an MRI knee needs an MRI room, a CT chest the CT room. A time is free when any suitable room is free. Add what the scheduler needs to know (a doctor’s order, implants, claustrophobia) and confirmations and reminders that never include health details.
2. Reports
The radiologist’s report is what the patient and their doctor act on. Show it clearly, as text and as the signed PDF, with the date and who read it.
3. Images in the browser
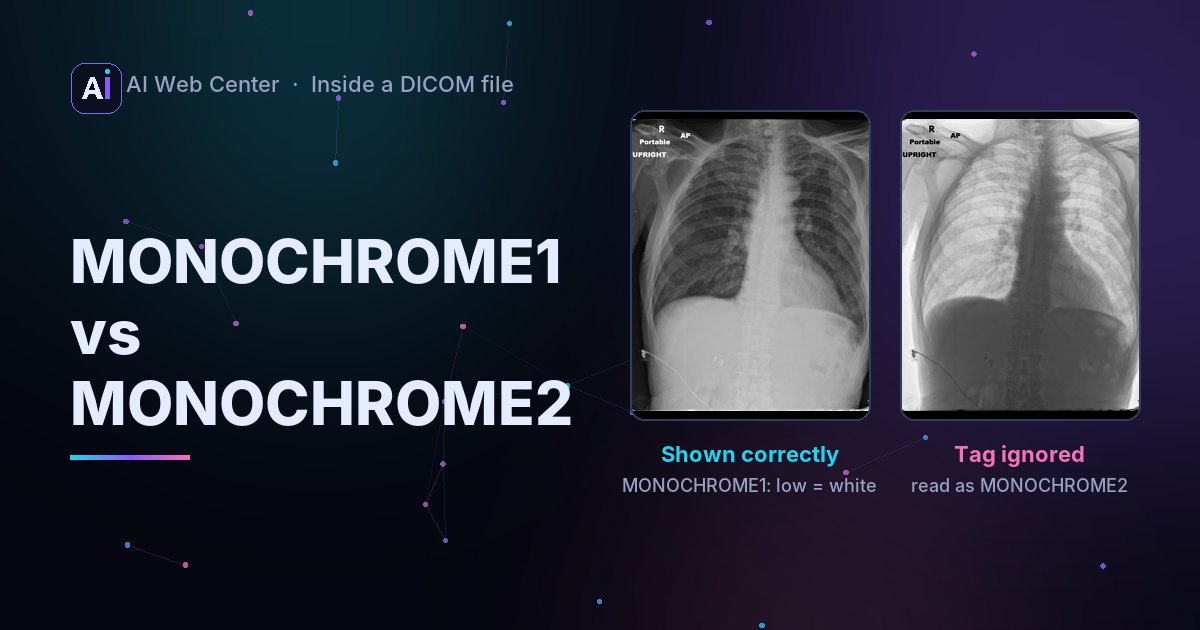
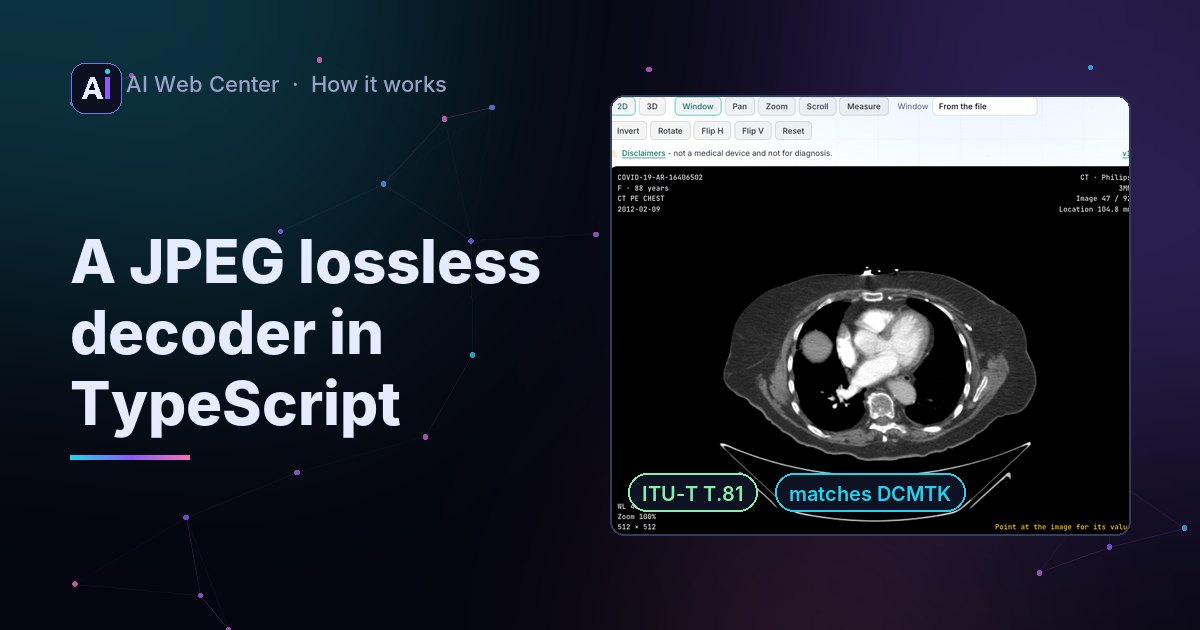
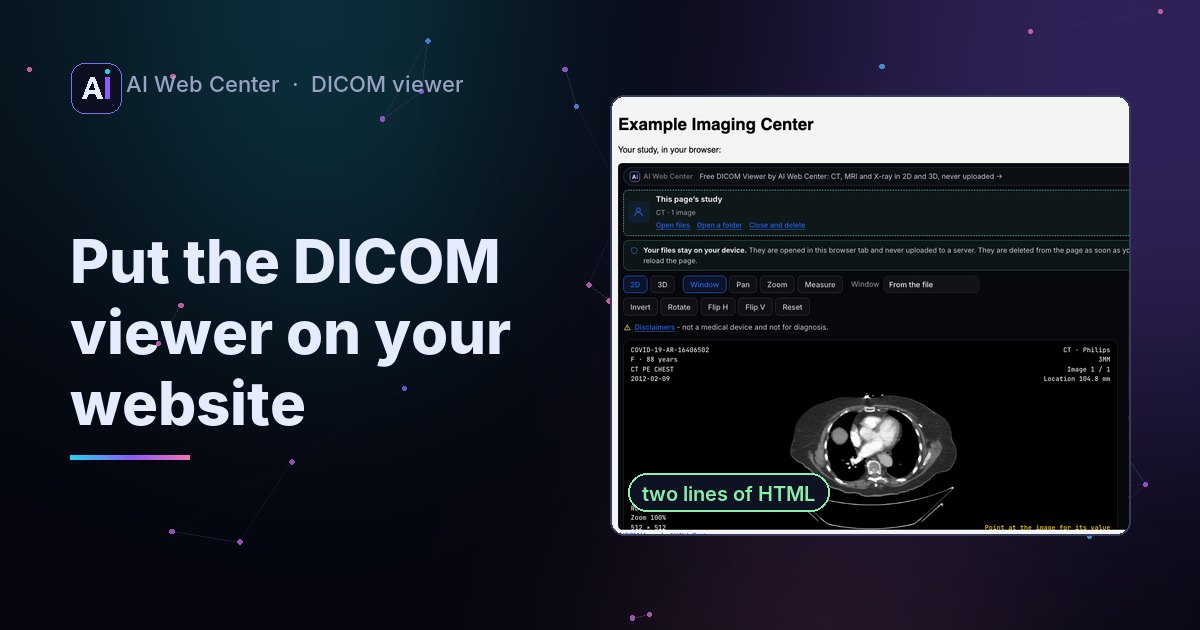
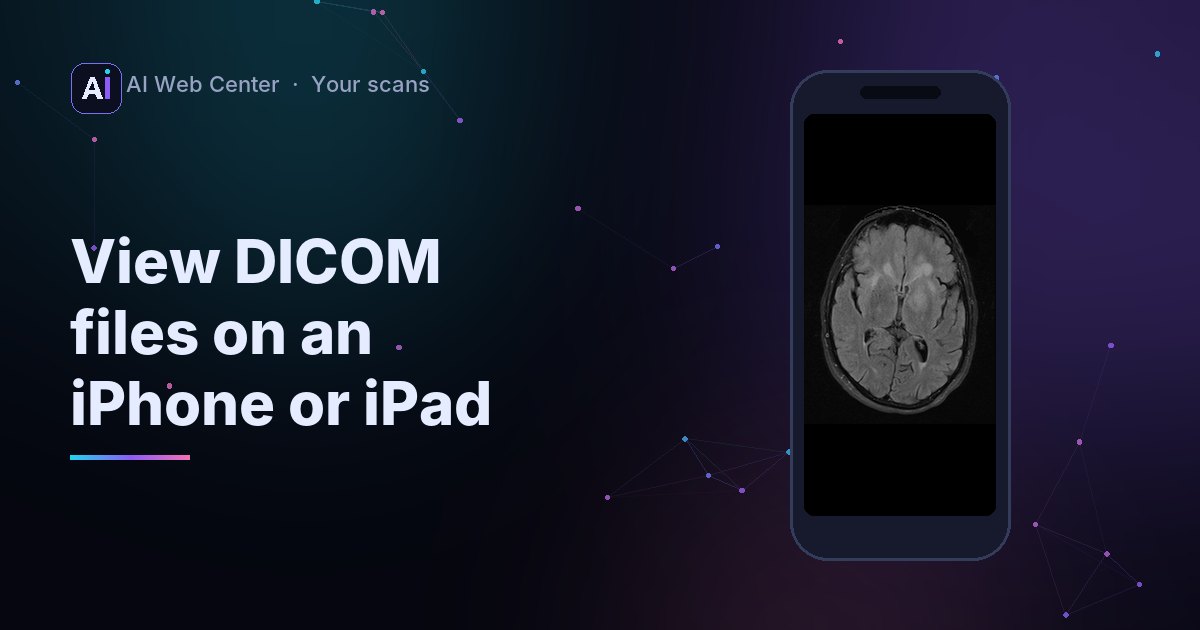
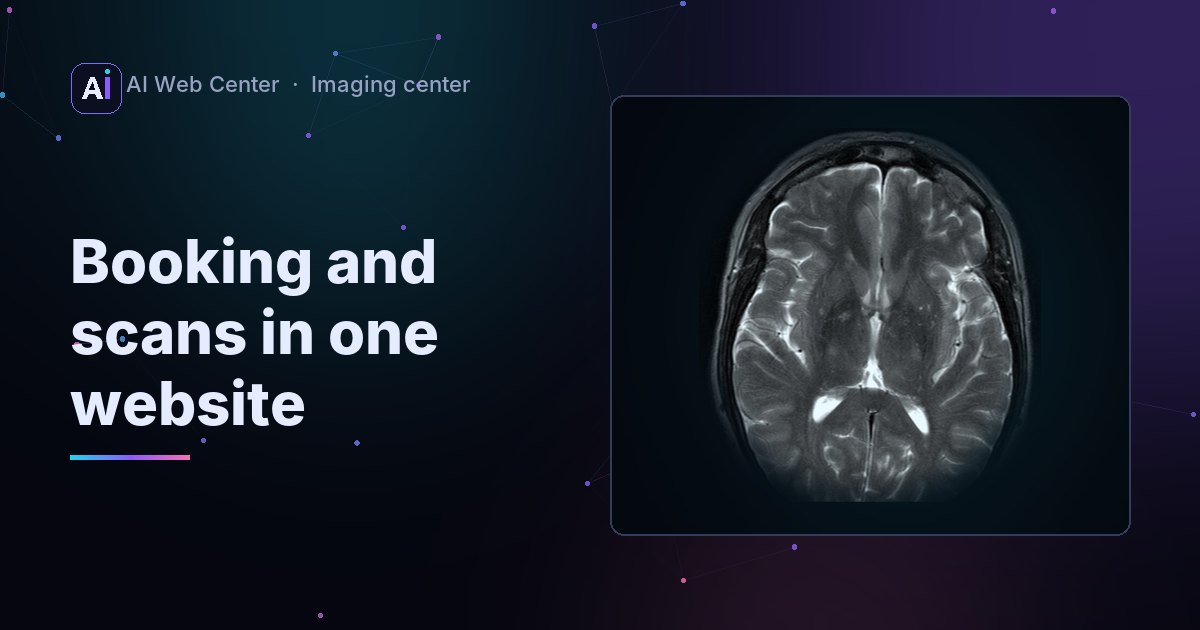
A browser DICOM viewer lets patients scroll through their own study, adjust the contrast and follow the report. No software to install, no CD. Say plainly that it’s for looking, not for diagnosis. The case study has our architecture.
4. Sharing with other doctors
The most practical feature: a link for a referring doctor or a second opinion, limited in time, revocable, and logged. Better than burning a CD. Patients who’d rather send files themselves need a clean download: the DICOM files in a ZIP, not screenshots. See how to send your scans to another doctor.
5. Prior studies from elsewhere
Patients arrive with CDs and ZIPs from other hospitals. Let them open those in the portal’s viewer, read in the browser and never uploaded, and, if the center wants them, upload them on purpose for the radiologist to compare.
6. The part nobody sees
- Sign-in with a second factor, and accounts for proxies (a parent, a caregiver).
- Access control: each patient sees only their own studies; each referring doctor only what’s shared.
- Audit logs of who viewed and shared what.
- Encryption in transit and at rest; no health details in emails, texts or URLs.
- Business associate agreements with every vendor that handles patient data. See the HIPAA post later in this series.
7. Connections
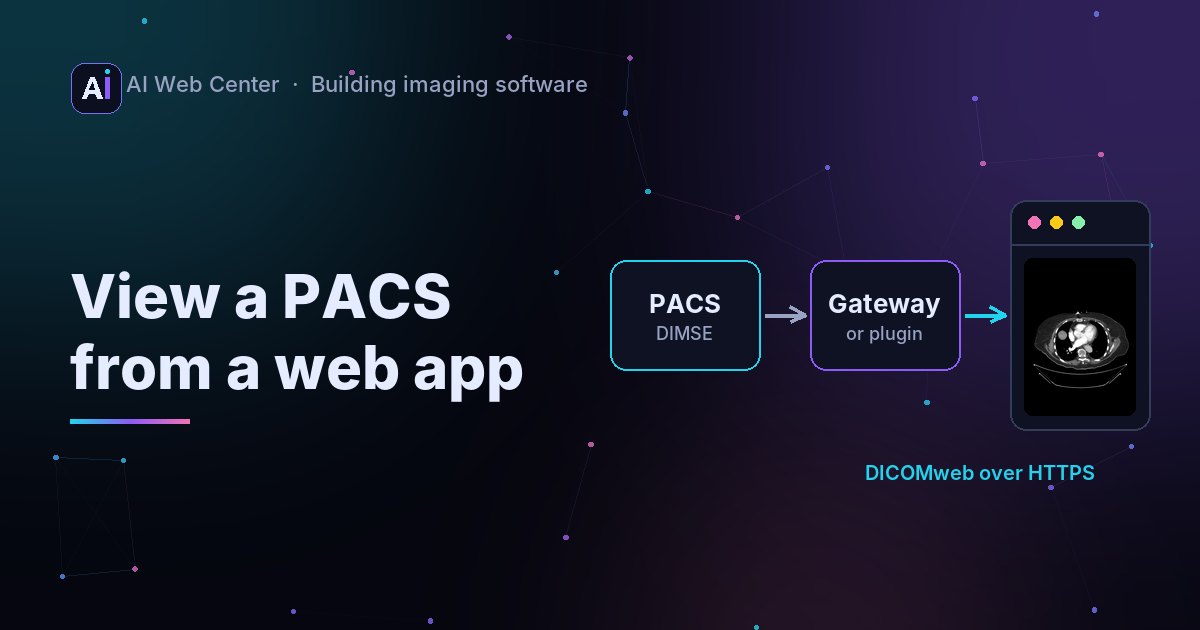
Behind the portal sit the scheduling system (RIS), the image archive (PACS) and the reporting system. DICOMweb, HL7 messages and plain APIs connect them; the next posts in this series cover the image side.
What to build first
- Booking and reports: the daily phone calls.
- Images in the browser, read from the archive.
- Sharing with doctors.
- Prior studies from CDs and ZIPs.
Key takeaways
- Booking by room and exam, not by person.
- Reports first, images alongside, clearly not for diagnosis.
- Time-limited, logged sharing beats CDs.
- Security, audit logs and agreements with vendors from day one.
Try the Lumenwell Imaging example →
We’re glad to share what we know. When you want a patient portal of your own, we’ll put all of it to work on your project, and because we build with AI-assisted development, it costs far less than you might expect. Let’s talk.
Frequently asked questions
Should patients see their images, or only the report?
Many patients want both, and they have a right to copies of their records. Show the report prominently; the images help them follow it and share them with other doctors. Say clearly that the viewer is for looking, not for diagnosis.
Does the portal need to store the images itself?
Not necessarily. It can show them from the center's archive (PACS) through DICOMweb or a gateway, keeping one copy of the images.
What's the most-used feature?
That depends on the center, which is why it's worth looking at what patients call about. Booking changes and getting images to another doctor are common reasons.